This guide explains Jaque and practical plaque-control approaches for healthier teeth. It provides objective background on how plaque forms, why “jaque” is often used in everyday Spanish to refer to dental plaque, and what clinicians focus on during prevention. You’ll also find an expert workflow, evaluation conditions, and FAQs to support better oral care decisions.
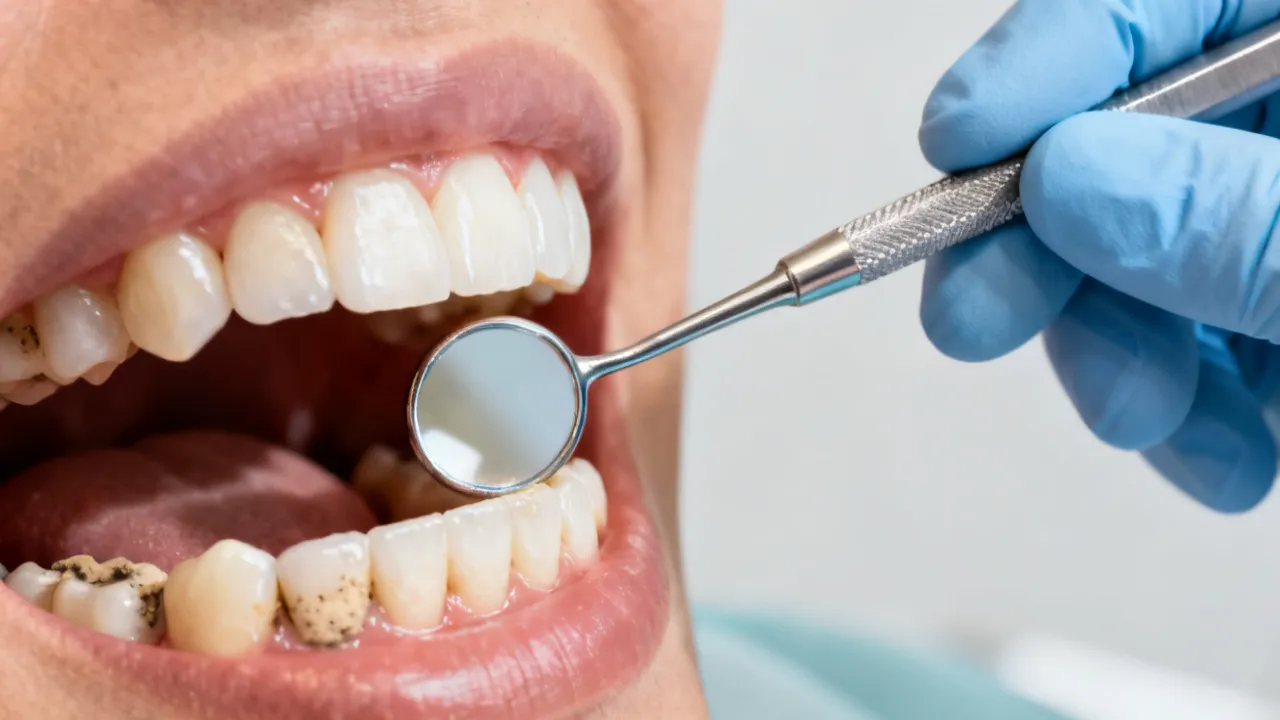
When people use the term Jaque in daily conversation, they are commonly pointing to dental plaque—the soft, biofilm layer that accumulates on teeth and gums. In clinical dentistry, the central priority is the same: reduce plaque formation, disrupt it effectively at home, and remove it safely in professional care. The goal is not cosmetic improvement; it’s to lower the risk of gingivitis, periodontal inflammation, enamel demineralization, and recurrent caries.
From an industry expert’s perspective, effective plaque control is a chain: biofilm management + accurate technique + appropriate tools + consistent follow-up. If any link is weak, plaque returns quickly—especially in areas that brushes miss, such as the gumline and between teeth.
In other words, “Jaque” is often shorthand for a biological process. You’re not just trying to “clean” your teeth in a vague sense—you’re trying to manage a living, dynamic community of microorganisms. That means plaque control must be repeated. It also means the plan should match your actual risk and the actual places plaque tends to accumulate in your mouth.
Plaque is a structured microbial community embedded in a protective matrix. It forms when oral bacteria metabolize carbohydrates from food and drink, generating acids and inflammatory byproducts. Over time, plaque can contribute to:
Crucially, plaque is not the same as calculus (tartar). Calculus is hardened plaque that usually requires professional instrumentation to remove. Prevention therefore focuses on stopping plaque before it mineralizes.
It can help to visualize the timeline. After eating or drinking, bacterial metabolism and biofilm formation can begin rapidly. If you don’t remove the biofilm regularly, it matures. Mature plaque behaves differently than fresh plaque: it becomes more structured, more adhesive, and more resistant. If that matured biofilm remains long enough, minerals in saliva deposit onto the plaque, creating calculus. Once calculus forms, the surface becomes rougher and bacteria can colonize it even more easily. That’s why “plaque control” and “calculus control” are linked, but not identical.
Additionally, plaque is not uniform. Different zones of the mouth host different environmental conditions: oxygen levels near the gums, saliva access, depth of grooves, and how food particles are retained. Because of that, the most effective home care is usually site-specific, not just “brush twice a day.”
Professionals don’t judge plaque control by habit alone. They assess outcomes and behavior patterns. A typical expert evaluation includes:
This matters because two patients can brush “the same number of times” yet have very different plaque retention locations. With “Jaque” framed as plaque, targeted correction is usually more effective than generic advice.
Clinicians also consider the severity and stability of inflammation. Some people have plaque but minimal bleeding because their tissue response is different; others bleed quickly because their immune response and microbial profile are more reactive. That’s why the outcome focus is important: you can assess plaque control by how the tissues behave, not only by what the patient says they do.
In many offices, clinicians use a combination of visual inspection, tactile assessment, and, when appropriate, periodontal measurements. While not every visit requires the same tests, the goal remains consistent: identify whether plaque is being removed sufficiently, whether calculus is present, and whether inflammation suggests that biofilm is persisting below the gumline.
In many practices—whether a private clinic or a preventive-focused dental program—plaque management proceeds in phases. While exact protocols vary by country and facility, the workflow is broadly consistent and grounded in evidence-based oral health guidance.
Think of plaque control as prevention plus feedback. Prevention means mechanical disruption of biofilm and fluoride exposure. Feedback means the clinician checks whether those efforts are working and then adjusts the plan if plaque or inflammation persists. Without feedback, plaque control often becomes a guessing game.
Another reason workflow matters is patient variability. Some patients have limited dexterity, some have orthodontic appliances, some have gum recession making certain surfaces more vulnerable, and some have high cavity activity. Tools and instructions must be matched to those realities. “One routine for everyone” typically fails the majority of patients—especially those who struggle with gumline coverage or interdental cleaning.
In practice, the “re-check” step is where many improvements happen. A common scenario is that a patient believes they brush correctly but the clinician observes persistent plaque at the same gumline location. Once the clinician identifies the problem—like brushing pressure that misses the margin, an angle that prevents bristles from contacting the junction, or interdental brushes that are consistently too large or too small—home care can be refined quickly.
Also, the workflow often includes motivational elements. Patients are more likely to keep routines when they understand the purpose. If they know that bleeding is a sign of inflammation driven by plaque biofilm, and that technique changes can make bleeding stop within a few days to weeks, adherence usually improves. The “why” is not a lecture; it’s a tool.
| Approach | What it targets | Best-fit conditions/requirements | Typical outcome focus |
|---|---|---|---|
| Fluoride toothpaste and correct brushing | Biofilm activity on tooth surfaces; supports enamel resistance | Daily consistency; correct coverage of gumline; not over-rinsing immediately after brushing | Lower caries risk and reduced plaque accumulation |
| Interdental cleaning (floss or interdental brushes) | Interproximal plaque where toothbrushes often miss | Proper size selection for interdental brushes; technique training; feasibility for the patient’s dexterity | Improved gum health and reduced interproximal biofilm |
| Professional cleaning/debridement | Existing plaque mineralized into calculus and tenacious deposits | When calculus is present or inflammation persists; scheduling based on risk assessment | Resetting the mouth’s biofilm environment |
| Adjunct antimicrobials (when clinically indicated) | Reduction of pathogenic load during specific needs | Guided by clinicians; appropriate duration; monitored for tolerance and outcomes | Short-term inflammation control alongside mechanics |
| Behavior and habit optimization | Consistency and technique reinforcement | Realistic routine design; follow-up if bleeding or high plaque persists | Long-term plaque management and stability |
This comparison helps clarify an important concept: different interventions target different stages and locations of the plaque problem. Fluoride supports caries prevention and helps tooth surfaces resist acid attacks; interdental cleaning focuses on the “hard to reach” biofilm reservoirs; professional removal addresses calculus and hardened deposits that home care cannot dissolve effectively; and adjunct antimicrobials provide a short-term boost when a patient’s condition requires extra microbial control.
However, none of these works optimally alone. If someone uses fluoride but never cleans between teeth, interproximal plaque remains. If someone flosses only occasionally, plaque can persist at the gumline and interproximal margins. If someone relies only on professional cleanings without improving technique, plaque and inflammation recur between visits.
You may see varying price information for toothbrushes, interdental devices, fluoride products, and professional maintenance packages. However, in plaque control, the decisive factor is clinical fit and repeatable technique, not marketing claims. Industry pricing often reflects material quality, ergonomics, brand formulation, and regional distribution. For example:
Supplier details in plaque control are typically best evaluated by looking at regulatory compliance in your region, transparent manufacturing practices, and documented product standards (e.g., where applicable). Since specific suppliers and local price sheets were not provided here, the most reliable approach is to obtain quotes from multiple clinics or reputable distributors and compare what’s included (exam, cleaning scope, follow-up, and risk-based maintenance).
It’s also useful to separate cost into categories. There’s the upfront cost of tools, but there’s also the “hidden cost” of inconsistency—time spent repeating ineffective routines, the discomfort caused by inflammation, and the long-term impact of untreated plaque leading to more complex therapy. From a preventive perspective, it can be more economical to invest in a routine that works quickly and is easy to maintain.
In other words, don’t pay only for a brand name. Pay for a configuration that you can use correctly every day. A mid-range tool that you can use for two minutes with accurate technique often outperforms a premium tool you abandon because it’s uncomfortable, awkward, or hard to maintain.
Professional care pricing can also be misunderstood. Some patients assume that every cleaning is the same. Clinically, the scope can differ based on deposits, inflammation, and risk. A patient with significant calculus or deeper inflammation will require different instrumentation and possibly staged appointments. When you compare prices, compare what the visit actually includes: assessment, removal technique, polishing, reinforcement, and follow-up planning.
Because Jaque is used as an everyday term in some Spanish-speaking contexts to refer to dental plaque, communication can improve when you align language during your visit. A practical way to reduce misunderstanding is to ask the clinician to confirm, in plain terms:
This “translation step” often leads to clearer home-care instructions and fewer gaps between what patients think they should do and what clinicians recommend.
Communication also helps with compliance because patients are more motivated when they understand what to target. If someone hears “plaque,” they may think it’s just a surface stain or an occasional “dirt.” But when they understand plaque as biofilm and see that biofilm produces inflammation, they recognize the routine as a health intervention. The same applies when patients hear “tartar” or “calculus”—understanding that calculus is hardened material they can’t remove at home usually increases trust in professional debridement schedules.
Another useful communication practice is to ask for demonstration. For instance, request that the clinician show how far the brush should angle toward the gumline, how much pressure to use, and how to position interdental cleaning without trauma. When the clinician demonstrates and the patient repeats, the chance of correct technique increases.
Even excellent products fail if requirements aren’t met. The following conditions are commonly necessary for meaningful improvement:
Consistency is sometimes misunderstood. Consistency doesn’t mean identical habits every single day for the rest of your life; it means maintaining a routine that you can actually do. A schedule with two minutes of brushing and targeted interdental cleaning most days is more likely to succeed than a plan that requires perfection.
Technique coverage is arguably the most common failure point. Many people brush “until it feels clean,” but plaque removal depends on bristles contacting the right surfaces with the right motion and time. That’s why clinicians often emphasize the gumline and the junction where plaque begins to inflame tissues.
Appropriate tool sizing deserves special mention because it affects both comfort and effectiveness. With interdental brushes, if the size is too small, it may not contact the space to disrupt plaque. If it is too large, it may cause bleeding and discomfort, leading to avoidance. Finding the correct size can be a turning point.
Risk-tailored planning is also essential because plaque control isn’t only about plaque—it’s also about what plaque does in your mouth. Dry mouth reduces saliva’s protective effects. Smoking affects gum tissues and immune responses. Frequent snacking increases acid exposure. Orthodontic appliances create new retention surfaces where biofilm thrives. Each risk factor modifies how aggressively you should manage plaque and how frequently you should seek professional maintenance.
When a dental team addresses “Jaque” (plaque) clinically, they usually combine mechanical removal with risk-based guidance. Depending on findings, appointments may include:
Important: professional cleaning is not a one-time cure. It resets the environment, but long-term stability depends on the patient’s ongoing mechanics and consistency.
Professional care often includes more than mechanical removal. Many teams also evaluate whether the patient is at risk for rapid plaque accumulation or whether inflammation signals a need for closer monitoring. If a patient has persistent bleeding despite reported brushing compliance, the clinician may suspect technique issues, tool mismatch, or untreated deposits. Sometimes the mouth needs a “reset” and an additional phase of care, such as targeted scaling or staged debridement.
Polishing can matter for comfort and surface characteristics. Rough surfaces make it easier for plaque and staining to accumulate. Polishing after deposit removal may not replace the need for home care, but it can support a smoother start to the maintenance phase.
When inflammation is present, professional care can also reduce microbial load and improve the local environment. But tissue healing requires that home care continues to disrupt new plaque formation. If a patient resumes poor technique immediately after a cleaning, inflammation often returns—sometimes even faster because the tissues may have become sensitive during the active phase.
To understand plaque control, it helps to understand the term biofilm. Plaque biofilm is not simply a layer of bacteria floating on a surface. It is an organized community surrounded by a matrix that helps protect microbes from mechanical shear and chemical attacks. That’s why brushing and interdental cleaning need to be mechanical: the goal is to physically disrupt the biofilm structure so the bacteria can’t maintain an intact protective environment.
Mechanical disruption does not require “scrubbing violently.” Gentle, controlled technique repeated consistently is often more effective and more sustainable. Many patients benefit from learning the correct angle and pressure so bristles can reach the gumline and remove plaque without causing abrasion or recession.
Fluoride supports the process by improving tooth resistance to acid attack. It does not automatically remove biofilm, but it can influence the mineral balance of enamel and help reduce caries risk. That’s why using fluoride toothpaste as prescribed is a foundational element of plaque control—especially for patients with a history of cavities or high sugar exposure.
Interdental cleaning is a mechanical “gap control” strategy. The toothbrush generally can’t reach the surfaces between teeth. That means plaque accumulates there unless floss or interdental brushes disrupt it. Since the gingiva often surrounds the interproximal areas, persistent biofilm between teeth can maintain inflammation even if the outer tooth surfaces look clean.
Professional debridement complements home care by removing deposits that are hardened or difficult to remove safely at home. It’s like removing the “starting material” that supports biofilm persistence. After professional removal, the home routine should be designed to prevent immediate reformation of plaque in the same retention sites.
Patients often want a simple solution—one product or one action that solves the problem. Plaque control is usually more nuanced. Below are frequent mistakes that lead to persistent “Jaque” and how clinicians address them:
In many cases, the “Jaque” conversation is helpful because it clarifies that persistence is expected if plaque continues to accumulate. It also reduces guilt: instead of thinking “I’m failing,” patients learn “I have specific retention sites to fix.” That mindset often improves adherence.
To control “Jaque” effectively, the routine has to fit the patient’s schedule, mobility, and motivation. Clinicians commonly help patients design a plan in three steps: simplify, standardize, and verify.
Simplify means choosing the smallest set of actions that cover the key retention areas. For most people, that includes: brushing at least twice daily with fluoride toothpaste and performing interdental cleaning once daily (or as clinically recommended).
Standardize means repeating the routine at predictable times. For example, some people do interdental cleaning at night because it becomes part of their bedtime routine. Consistency often matters more than the exact timing.
Verify means using feedback to confirm the routine works. Clinicians may check tissue response or plaque presence. Patients can also use visual tools like plaque-disclosing agents (when recommended) to see where plaque remains after a routine. Seeing “where Jaque is” can convert vague effort into targeted improvement.
In daily life, you can also plan for interruptions. If you’re traveling, you may not have access to your exact products. Clinicians often recommend carrying a travel kit with a toothbrush, fluoride toothpaste, and the chosen interdental method. If you can’t do the routine perfectly one day, the most important thing is to resume as soon as possible—don’t abandon the entire routine.
While brands vary, clinical criteria for tool selection are fairly consistent. The goal is to select tools you can use with correct technique consistently and comfortably.
Toothbrush choice often involves head size, bristle softness, and the ability to achieve controlled contact at the gumline. For some people, an electric toothbrush can help with consistency of motion and time, especially if the patient struggles with manual technique. However, an electric toothbrush is not magic; it still requires the correct technique and routine. A manual brush can work very well if the patient can angle and position it properly and cover all relevant surfaces.
When discussing toothbrushes, clinicians also consider whether the patient has sensitivity. If brushing triggers discomfort, patients often brush more lightly and may skip gumline contact—leading to increased retention of plaque. In those cases, clinicians may recommend softer bristles, modified technique, desensitizing strategies, or temporarily adjusting the routine to reduce inflammation while improving coverage.
Interdental cleaning is often the most individualized component of plaque control. Interdental brushes are frequently favored when spaces allow them, because they can disrupt plaque while being easier to use for many patients. Floss can be effective for smaller spaces or when the anatomy makes brushes difficult. However, floss requires technique and consistent patient compliance.
A common clinical pattern is that patients try a “standard” size or a random method and struggle. The solution is not “do more” but “choose the right fit.” When interdental brush sizing is optimized, comfort improves and plaque control improves simultaneously.
Another consideration is orthodontic appliances. Braces and aligners can create additional retention sites along brackets and around appliance edges. Clinicians may recommend specific brushes, floss threaders, or water-based adjuncts in some cases. The key is that any adjunct should support mechanical disruption, not replace it entirely.
Adjunct antimicrobials—such as certain mouthrinses—are sometimes used as part of plaque control strategies when clinically indicated. These are typically most relevant when inflammation is difficult to control with mechanical cleaning alone, or when there is a specific risk situation. However, adjuncts cannot replace brushing and interdental cleaning.
If someone uses an antimicrobial rinse but never removes biofilm mechanically, plaque can still persist. The rinse might temporarily reduce microbial load or improve symptoms, but the underlying retention sites remain. That’s why clinicians generally view adjuncts as supportive tools within a broader plaque-control system.
Adjuncts may also have limitations. Some are not ideal for long-term daily use without guidance due to side effects or because the underlying mechanical problem persists. The responsible clinical approach is to use adjuncts for the right duration, guided by evaluation, and then transition back to the core mechanical routine.
“Jaque” is common to everyone, but not everyone’s risk profile is the same. Clinicians prioritize plaque control more aggressively when they see factors that increase biofilm formation, reduce saliva protection, or increase tissue vulnerability.
Saliva helps buffer acids, supplies minerals, and supports oral clearance. When saliva decreases, biofilm can accumulate more easily and acid exposure may have a greater impact. People with dry mouth may need tailored advice on hydration, saliva substitutes, and careful fluoride strategy.
It’s not only what you eat, but how often you eat or sip. Frequent carbohydrate exposure provides more “fuel” for bacterial metabolism and acid production. Plaque control becomes even more important when dietary frequency is high. In clinical guidance, it’s common to combine oral hygiene with dietary counseling—reducing frequency of sugar exposure and improving timing.
Braces create additional surfaces and small niches where plaque adheres strongly. Patients typically need more detailed interdental cleaning strategies and may benefit from specialized brushes. The earlier patients learn to manage plaque around appliances, the lower the risk of gingivitis during treatment.
Smoking can alter the oral microbiome and impair immune responses and tissue healing. It is associated with more severe periodontal outcomes in many clinical studies and also increases plaque’s harmful impact. In such cases, clinicians emphasize plaque control as part of a broader risk-reduction approach.
If someone has had periodontitis, tissue response and microbiological profiles may differ, increasing the importance of maintenance. Plaque control remains critical, but professional maintenance intervals might need to be shorter. Patients with prior periodontal disease often benefit from detailed feedback and close follow-up.
Patients often measure success by “no more bleeding” or “less staining.” Clinically, success is broader. A successful plaque-control plan usually leads to:
Importantly, early improvements can happen quickly, especially for gingivitis driven by plaque. Many patients notice decreased bleeding within weeks once technique is corrected. If bleeding persists, that’s a sign the biofilm disruption isn’t adequate yet or deposits remain.
Sometimes the mouth needs time. If a patient’s tissues are inflamed, aggressive changes can cause temporary irritation. That’s why clinicians may adjust technique gradually, reduce trauma, and monitor healing. The goal is steady improvement rather than sudden overcorrection.
Occasionally, people do their best at home and still experience persistent issues. In such cases, they may need professional evaluation to rule out deeper problems such as calculus retention, periodontal pocketing, or other causes of inflammation and bleeding.
Examples of red flags that warrant closer evaluation include:
These are not “failures.” They are signals that plaque control strategy may need adjustment or that professional debridement or additional therapy is necessary. In fact, persistent issues are often exactly what makes follow-up so valuable: clinicians can identify retention sites and deposits that home care cannot manage.
If you want to use the term Jaque in a way that clarifies your concern, you can ask questions that connect the daily term to clinical evaluation. This improves shared understanding and helps create a tailored plan. You can use prompts like:
Clinician-patient clarity reduces confusion and helps the routine become measurable. It also supports patient confidence: if you know what to look for, you can track whether your plan is working.
In everyday Spanish usage, Jaque is often a reference to dental plaque—a soft microbial biofilm that accumulates on teeth and near the gums. Clinically, plaque control focuses on reducing biofilm buildup and the inflammation it can trigger.
Soft plaque often appears as a film or residue that accumulates quickly. Calculus (tartar) tends to feel rough and can form even if you brush well. Only a clinician can confirm deposit type reliably during an exam.
You can still observe clues at home. If you notice roughness that seems to return quickly after cleaning, calculus may be involved. If you notice a thin sticky residue that wipes away more easily, plaque is more likely. However, these are indicators, not diagnoses. The safest approach is to have deposits evaluated because the treatment differs.
Both matter, but interdental cleaning is critical because toothbrush bristles commonly miss interproximal surfaces. In many patients, adding consistent interdental cleaning produces a noticeable improvement in gum health—especially where bleeding occurs.
For people who currently do little interdental cleaning, the most practical starting goal is often to choose one daily target moment. For example: “I will clean between teeth every night before bed.” Once that becomes consistent, the routine can be refined by technique and tool selection.
Not automatically. Effectiveness depends on fit, correct use, and consistent routine. A properly sized interdental brush or a toothbrush that you can use with accurate technique can outperform a costly product used incorrectly.
Sometimes higher-priced items are more ergonomic or easier to use, which can indirectly improve adherence. That’s a different mechanism than “stronger cleansing.” The key is usability and technique consistency.
Frequency should be based on your risk profile (for example, gum inflammation history, tendency for calculus, smoking status, and cavity risk). Many patients do best with a clinician-recommended maintenance interval rather than a universal schedule.
Some patients with low risk may require less frequent maintenance, while others—especially those with periodontal risk—may benefit from shorter intervals. Your clinician can determine this based on clinical findings and your ability to maintain plaque control at home.
Adjuncts may reduce microbial load temporarily, but they cannot replace mechanical removal and correct brushing plus interdental cleaning. Plaque management remains fundamentally technique-driven.
A useful way to frame it is: adjuncts support the routine; they don’t substitute for it. If a patient tries to replace brushing entirely, plaque tends to regrow, inflammation may persist, and calculus may form more quickly.
Dental guidelines consistently emphasize biofilm disruption through mechanical cleaning and fluoride use for caries prevention, alongside professional maintenance when indicated. For general evidence and public guidance, reputable references include organizations such as the American Dental Association (ADA) and the World Health Organization (WHO). (See sources below for more context.)
In clinical research, plaque control interventions are often evaluated by outcomes such as gingival bleeding, plaque scores, and caries incidence. While study designs vary, the broad consensus aligns with the practical workflow described here: consistent mechanical cleaning plus fluoride, with professional maintenance based on risk.
Yes, when halitosis is related to biofilm activity, improving plaque control can reduce odors. However, persistent bad breath can also have other causes (e.g., ENT issues), so clinician evaluation is helpful.
It’s also possible that halitosis has multiple contributors. A plaque-focused routine can reduce one source of odor, but if there is chronic tonsil-related issues, sinus problems, or gastrointestinal contributors, additional evaluation may be needed. That’s why comprehensive assessment matters, especially when odor persists.
Understanding Jaque as dental plaque reframes the problem from vague “cleaning” to a clear, biological target: disrupt the biofilm, remove deposits when present, and sustain the routine with technique you can actually maintain. If you approach plaque control as an ongoing system—home mechanics plus professional risk-based maintenance—you create conditions for steadier gum health and reduced caries risk over time.
Ultimately, the best plaque-control plan is the one you can repeat and refine. When patients and clinicians align language, identify retention sites, and choose tools that fit anatomy and lifestyle, plaque control becomes a measurable process rather than a daily struggle. That’s the practical meaning of “Jaque”: once you know where plaque persists, and why it persists, you can take targeted action and improve outcomes.




Este guia contextualiza quem é Rozinalva Mendes no cenário de planejamento e organização de serviços, com foco em critérios de qualidade, conformidade e tomadas de decisão. De modo objetivo, o texto apresenta o significado prático do termo “planejamento” e como ele se aplica a rotinas, fornecedores e acompanhamento. Também organiza requisitos, etapas e comparações para apoiar escolhas mais consistentes.

Este guia reúne, de forma profissional e objetiva, informações sobre Rozinalva Mendes, orientando a leitura do contexto, critérios de escolha e boas práticas de cuidado. Em seguida, apresentamos dados de referência e análises que ajudam a interpretar a relevância do nome nos processos e na tomada de decisão, com foco em requisitos, condições e riscos a evitar.

Este guia analisa, de forma objetiva, quem é Rozinalva Mendes e como seu nome aparece em buscas ligadas a atendimento, orientação e credibilidade. Em seguida, contextualiza o papel de profissionais no setor de serviços e o que costuma ser relevante para quem procura suporte confiável, incluindo critérios de verificação, expectativas de qualidade e organização da decisão.

Este guia orienta sobre como entender e organizar informações profissionais relacionadas a Rozinalva Mendes, com foco em critérios de avaliação, seleção de serviços e conformidade. Em seguida, apresenta um panorama objetivo do contexto por trás do nome e das palavras-chave, explicando como interpretar referências, fontes e condições necessárias para uma decisão bem fundamentada.

Este guia analisa, de forma objetiva, o contexto e os cuidados ao considerar Rozinalva Mendes em processos de parceria e apoio técnico. Ao longo do texto, você encontra fundamentos de mercado, critérios de avaliação e requisitos comuns do setor, além de um quadro comparativo, passo a passo de verificação e respostas a perguntas frequentes sobre fornecedores, conformidade e alinhamento de expectativas.

Este guia organiza, de forma objetiva, informações sobre Rozinalva Mendes e como isso se relaciona com práticas de cuidado, orientação e tomada de decisão. Em seguida, contextualiza o tema com base em fundamentos do setor, explicando o que observar ao buscar serviços, critérios de qualidade e como avaliar condições e requisitos com segurança. Atenção: como “Rozinalva Mendes” é um nome de pessoa, as referências concretas dependem de dados verificáveis.

